
Jul 30
Jul 30
Jul 29
Jul 22
Jul 19
Jul 17
Brushing your teeth is something we do every day, yet many people still use incorrect techniques that harm their enamel, irritate their gums, or miss key areas of the mouth. This article breaks down the dentist-approved brushing methods that truly make a difference—explaining why technique matters more than force, how timing and angles affect plaque removal, and how AI-powered tools like BrushO can reinforce these best practices in your daily routine.
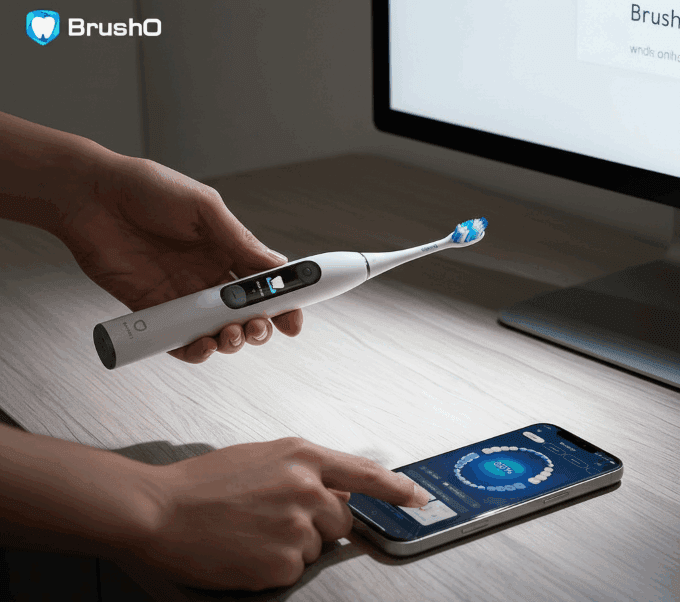
Brushing isn’t just about going through the motions—it’s a technique-sensitive practice. According to the American Dental Association (ADA), poor brushing habits can lead to:
• Gum recession from excessive force
• Missed plaque in hard-to-reach areas
• Enamel erosion due to incorrect motion
• Increased risk of cavities and gingivitis
Good brushing technique removes plaque effectively without damaging your gums or enamel—and when practiced consistently, it’s your best defense against dental problems.
Most dentists recommend the Modified Bass technique, especially for those concerned about gum health:
• Hold the brush at a 45-degree angle toward the gumline
• Use small circular or vibrating motions, not back-and-forth scrubbing
• Gently brush the gumline to dislodge plaque from where it hides
• Brush each section (inner, outer, and chewing surface) for optimal results
This method is gentle, thorough, and prevents gum damage while cleaning efficiently.
Time matters. Studies show that most people only brush for 45–70 seconds—far less than the recommended 2 minutes. Use a timer or a smart toothbrush that guides you through each zone.
Dentists recommend dividing your mouth into four quadrants or more advanced six zones (BrushO’s method) to ensure complete coverage:
• Upper Right
• Upper Left
• Lower Right
• Lower Left
Or with BrushO: 6-zone, 16-surface tracking ensures no area is missed, especially behind molars or along the gumline.
Brushing harder doesn’t mean cleaner teeth—in fact, excessive force leads to gum recession and enamel wear. Most dentists advise using just enough pressure to feel the bristles against the gums without bending them. Smart toothbrushes like BrushO include real-time pressure sensors, alerting you when you’re pressing too hard.
Neglecting the inner surfaces of teeth (especially the bottom front teeth) is a common mistake. Tilt your brush vertically and use up-and-down strokes on the inside surfaces of front teeth.
Dentists prefer soft-bristled brushes with rounded tips. BrushO offers interchangeable heads with ADA-compliant softness for sensitive teeth and gums.
BrushO is designed to coach and reward optimal brushing habits through:
• Real-time feedback: Pressure alerts, zone guidance
• AI-powered brushing analysis: Shows missed spots and brushing angles
• Daily reports and habit tracking
• “Brush & Earn” reward system to encourage consistency
With BrushO, the best dentist-recommended techniques become part of your everyday routine.
• Replace your brush head every 3 months
• Floss before brushing for better plaque removal
• Rinse with fluoride mouthwash afterward
• Avoid brushing right after acidic meals—wait 30 minutes
The best brushing technique isn’t just about effort—it’s about intention, form, and feedback. By adopting dentist-recommended practices like the Modified Bass technique, brushing gently with proper angles, and ensuring full coverage, you’ll dramatically improve your oral health. With smart tools like BrushO, you’re not just brushing—you’re learning, improving, and earning rewards for healthier habits. Make your brushing smarter and more effective—your smile will thank you.
Jan 29
Jan 29
Jul 30
Jul 30
Jul 29
Jul 22
Jul 19
Jul 17

Maxillary transverse deficiency is a common problem in adolescent and adult patients, and while rapid palatal expansion works well in the growing child, the mature midpalatal and circummaxillary sutures resist conventional expansion. Surgically assisted rapid palatal expansion, commonly abbreviat...

The position of the screw access channel is the hidden geometry that decides whether a screw-retained implant crown looks natural or fails esthetically. In the anterior zone the access hole must be brought to the lingual or palatal surface; in the posterior zone it can rest on the occlusal table....

The grafting of a deficient ridge was long seen as a mandatory step before implant placement, and classic teaching recommends a bone graft whenever the residual volume is small. In the same period, a simpler philosophy has matured: in a large share of cases, a favorable site can host an implant w...

The premature loss of a primary tooth is a common event in the growing child, and the premature loss of the primary first molar before its successor is ready is a particular problem. The loss of the primary first molar often passes without obvious symptoms, but the consequences for the permanent ...

The gingival biotype describes the thickness and the contour of the gingiva around a tooth or an implant, and it strongly influences the prognosis of every restorative and periodontal procedure. A thin, scalloped biotype is fragile: recession follows minimal trauma, the soft tissue shows through ...

The eruption of the primary teeth is one of the earliest milestones of craniofacial development, and it matters to the pediatric dentist for more than its visual charm. The pattern in which the deciduous teeth appear establishes the arch form, guides the chewing development, and lays the groundwo...

The removal of mandibular third molars is among the most common operations in oral and maxillofacial surgery, and it carries a small but serious risk of damage to the lingual nerve. Injury to this nerve is disabling out of proportion to its frequency, because it produces numbness, altered taste, ...

The mandibular second molar is considered less often than the third molar in discussions of impaction, yet when it fails to erupt the consequences can be substantial. A retained second molar undermines mastication, invites caries and periodontal disease in the adjacent teeth, and can trigger root...

The final crown on a dental implant can be attached to the abutment in two fundamentally different ways: by a screw that passes through the crown into the implant, or by dental cement that bonds the crown onto an abutment. The choice between screw-retention and cement-retention is one of the earl...

Apical periodontitis is not primarily a disease of the periapical bone but an inflammatory response to an infection that originates inside the root canal. The periapical lesion is a host reaction to bacteria delivered through the apical foramen, so treatment must eliminate the microbial source. T...

BrushO AI Electric Toothbrush offers real-time brushing guidance, pressure feedback, coverage tracking, and app-based progress reports for a cleaner daily routine.
BrushO AI Electric Toothbrush offers real-time brushing guidance, pressure feedback, coverage tracking, and app-based progress reports for a cleaner daily routine.


Address: RM 1427, 14/F RADIO CITY 505, HENNESSY RD CAUSEWAY BAY, HONG KONG
Code: 000000
Phone: +852-53758652
Email: customerservice@brusho.com